How Long Does PCP Stay in Urine? Detection Windows Explained
How long does PCP stay in urine? For most people, a urine test can first pick up phencyclidine about 4 to 6 hours after use. It can stay positive for roughly 7 to 14 days after the last use, according to FDA guidance on drugs of abuse tests. That range is a guideline, not a promise. Dose, how often someone uses, metabolism and body composition can all move the window in either direction.
We supply rapid urine drug test cups to clinics, behavioral health programs, employers, drug courts and corrections. This guide is written for the people who run those programs and have to interpret the result in front of them.
TL;DR
- Urine can first show PCP about 4 to 6 hours after use, and a positive can last 7 to 14 days after the last use (FDA).
- One reference laboratory describes PCP as detectable for up to 8 days, with an average half-life of 15 hours (Mayo Clinic Laboratories).
- Heavy or long-term use, body fat and urine pH can change the window. No single number fits everyone.
- A rapid cup result is a preliminary screen. Positives need confirmation by GC/MS or LC-MS/MS before anyone acts on them.
- Of our cups, only the 12-panel PCP cup is CLIA-waived and FDA-cleared. The 12-panel ETG/fentanyl, 14-panel and 16-panel cups are Forensic Use Only.
Table of Contents
- How long PCP stays in urine, by source
- What changes the detection window
- What a positive PCP result does and doesn’t tell you
- Screening versus confirmation
- False positives: why confirmation is not optional
- Where our cups fit
- Our perspective
- A practical timeline for program staff
- Collecting a defensible specimen
- Ordering PCP-capable cups for a program
- FAQ
- Sources
How long PCP stays in urine, by source
Different sources give different numbers because they measure different things: the point of first detection, the point of last detection, or the exposure period a laboratory result implies. Here is how the most reliable ones line up.
| Source | What it says | Notes |
|---|---|---|
| FDA | Urine can first detect PCP about 4 to 6 hours after use. A positive can last 7 to 14 days. | Described as a guideline only |
| Mayo Clinic Laboratories | PCP or its metabolites may be detected for up to 8 days. | Approximate table uses a 25 ng/mL limit of quantitation |
| Mayo Clinic Laboratories | A result above the reporting threshold points to exposure about 2 to 8 days before collection. | Average clearance half-life of 15 hours |
Read together, the practical picture is this. After occasional use, a urine screen is most likely to turn negative within about a week. After repeated or heavy use, it can stay positive into the second week. Longer figures circulate online, some of them very long. We treat them as outliers unless they come from a laboratory or regulator, and we don’t build program policy on them.
The lower end matters too. A urine test collected within the first few hours may be negative simply because the drug has not yet reached the urine in measurable amounts. FDA notes that a sample can be collected too early or too late, and that a negative result does not prove a person never used a drug (FDA).
What a half-life of 15 hours means for a test
Half-life is the time the body takes to clear half of a substance from circulation. Mayo Clinic Laboratories reports an average PCP clearance half-life of 15 hours (Mayo Clinic Laboratories). A drug does not vanish after one or two half-lives. Concentrations keep falling, and the test turns negative when the concentration drops below the cutoff.
That is why the cutoff matters as much as the drug. A screening cup is built around a defined concentration. Our PCP drug test cups page lists a 25 ng/mL panel. A laboratory method with a lower threshold could find the drug later than a rapid cup does, and a higher threshold would find it for a shorter time.
What changes the detection window
The ranges above are averages. Several factors push an individual result earlier or later.
- Amount and frequency of use. More drug and more frequent use generally mean a longer window. FDA says timing can vary with how long and how much a person has used PCP, and with metabolism (FDA).
- Body fat. PCP accumulates in fatty tissue. A drug-free workplace reference notes that chronic users, physically inactive users and people with high body fat may have longer detection periods (Drug Detection Windows).
- Metabolic rate, age and overall health. The same reference lists these among the factors that affect detection times, along with urine pH (Drug Detection Windows).
- Urine pH. A Mayo Clinic Laboratories confirmation listing notes that urine PCP may be undetectable at alkaline pH (Mayo Clinic Laboratories). For a program, this is one reason a single negative does not close the question.
- Test type and cutoff. A rapid immunoassay cup, a laboratory immunoassay and a mass spectrometry method can each draw the line in a different place.
- Collection timing. The gap between last use and the sample is the biggest variable, and it is usually the one nobody knows for sure.
We don’t cover ways to alter or defeat a test, and we won’t. Programs that test fairly rely on supervised collection, a temperature check and confirmation of positives. That is also why every cup we sell carries an integrated temperature strip.
What a positive PCP result does and doesn’t tell you
A positive urine result shows that PCP or a related target was present in the specimen. It says less than people often assume. The Ohio State University laboratory notes that detection in urine indicates recent exposure but cannot determine the dose or the route of administration (Ohio State labs).
It also does not measure impairment at the moment of the test. A person can test positive days after any effect has worn off. A person can also be affected shortly after use and test negative, because the drug had not yet reached the urine at detectable levels.
For a clinic or court program, the useful questions are narrower:
- Was the collection observed and the specimen temperature in range?
- Is the result preliminary or confirmed?
- Does the person’s medication list explain a cross-reaction?
- What does program policy say about a presumptive positive?
Screening versus confirmation
A rapid cup is a screen. SAMHSA describes screening as usually qualitative and based on a rapid immunoassay that can cross-react with chemically similar substances. Confirmation uses a more specific, usually more sensitive laboratory method that identifies and quantifies the particular drug or metabolite (SAMHSA, Clinical Drug Testing in Primary Care).
Laboratories follow this pattern in practice. ARUP Laboratories, for example, runs a qualitative enzyme immunoassay PCP screen and, if the specimen screens positive, confirms and quantifies it by LC-MS/MS (ARUP Laboratories).
So the workflow is simple to state:
- Negative screen: record it. Remember that a negative does not guarantee a person has not used drugs, since FDA cautions that no drug test is 100% accurate (FDA).
- Presumptive positive: treat it as preliminary. Send the specimen for GC/MS or LC-MS/MS confirmation before any adverse decision.
False positives: why confirmation is not optional
PCP is one of the analytes where a screen can flag something that is not PCP. A published case report found false-positive PCP immunoassay results associated with desvenlafaxine, venlafaxine, dextromethorphan, ibuprofen and tramadol, and GC/MS found no PCP in the reported cases. The authors also suggest such false positives may become more common as desvenlafaxine use rises (PMC, 2017).
The scale is not trivial. In one hospital study, 17.9% of preliminary positive PCP urine screens failed to confirm by GC/MS (PMC). That is one institution’s experience, not a universal rate, but it shows why a rapid positive should never stand alone.

If a donor’s result is positive and they report taking one of those medications, document it and let the confirmation decide. Programs that handle immigration or regulatory medical paperwork face similar questions about medications that cross-react with PCP screens, and the answer is the same: record the medication, then confirm.
Where our cups fit
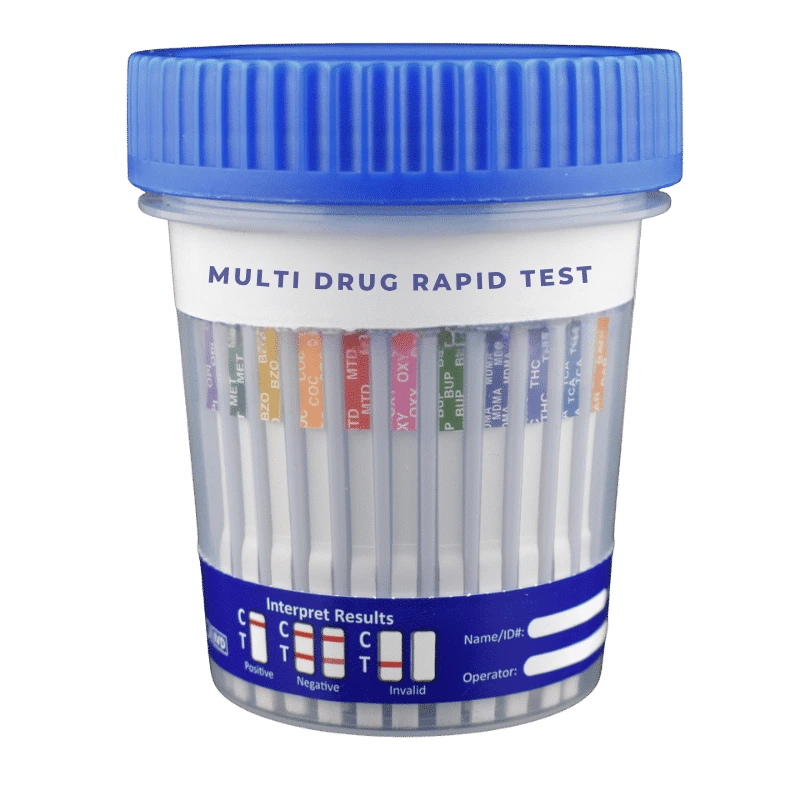
If your program screens for PCP, the cup you choose determines both what you can claim and who can use it. Here is how our four cups line up. Each has an integrated temperature strip and a rapid read in about five minutes.
| Cup | Regulatory status | Notes |
|---|---|---|
| 12-panel cup with PCP | CLIA-waived, FDA-cleared | Point-of-care use |
| 12-panel cup with ETG and fentanyl | Forensic Use Only, not CLIA-waived | Alcohol and fentanyl screening |
| 14-panel cup with PCP, ETG and fentanyl | Forensic Use Only, not CLIA-waived | Adds PCP, alcohol and fentanyl |
| 16-panel cup | Forensic Use Only, not CLIA-waived | Adds kratom and TCA |
This distinction matters for compliance. A CLIA-waived cup can be used at a point-of-care site holding the right certificate. Forensic Use Only cups are intended for programs that treat the result as a presumptive screen feeding confirmation, such as many court, corrections and monitoring programs. If you are weighing the certificate question, our guide on how to get a CLIA waiver certificate covers the steps, and the CLIA-waived cups page explains which product fits.
For background on the analyte itself, see what PCP is on a drug test, and for how other drugs compare, our drug detection times chart. If you are still choosing between panel sizes, 12 vs 14 panel lays out the drug lists.
Our perspective
We get one question from buyers more than any other: “If someone tested positive for PCP, when did they use it?” Our honest answer is that the cup cannot tell you. It tells you whether the sample crossed the cutoff on the day you collected it. Everything else is inference from published ranges, and those ranges are wide.
That is why we build our materials around two habits. First, we state clearly which cups are CLIA-waived and which are Forensic Use Only, so a program never buys a cup for a use it was not cleared for. Second, we describe every result as preliminary. A positive goes to GC/MS or LC-MS/MS. A negative is a data point, not proof.

We also think programs are better served by quoting ranges than by quoting a single number. When a counselor or a case manager says “PCP clears in three days,” that sets up a bad conversation with a client who then tests positive on day ten. Saying “most people clear in about a week, some take two, and your result is preliminary until the lab confirms” is accurate and protects everyone.
The 12-panel PCP cup is our option for point-of-care programs that need a CLIA-waived, FDA-cleared test. For programs that also need alcohol (ETG) and fentanyl on the same cup, the 14-panel is built for that, as a Forensic Use Only product. We would rather you pick the right cup than the biggest one.
— Alina
A practical timeline for program staff
The table below turns the published ranges into a working reference. It is not a prediction for any one person.
| Time since last use | What a urine screen is likely to show | Comment |
|---|---|---|
| 0 to 4 hours | May be negative | Too early for detection in many cases (FDA) |
| About 4 to 6 hours | First detectable | FDA’s stated onset |
| 2 to 8 days | Commonly positive | Laboratory exposure window (Mayo Clinic Laboratories) |
| 7 to 14 days | Can still be positive | FDA’s upper range, more likely after heavy or repeated use |
| Beyond 14 days | Uncommon, not impossible | Rely on confirmation and clinical context |
Two cautions apply when using this table. First, repeated use stretches the window, and body fat can lengthen it further. Second, the table says nothing about when impairment occurred, only about whether a target was present.
Collecting a defensible specimen
Detection windows are only useful if the specimen is genuine and handled well. FDA notes that test performance and storage can affect results (FDA). A short checklist for staff:
- Confirm the donor’s identity and explain the procedure.
- Collect the sample in the cup and check the temperature strip right away.
- Read the result in the time window in the instructions. Do not read it later.
- Record the result, the time, the lot number and the staff member.
- If the screen is positive and the decision matters, send the specimen for laboratory confirmation. Keep the chain-of-custody paperwork your program requires.
- Document any medications the donor reports.
The lot number and expiry matter more than people expect. A cup past its expiration date or stored outside its labeled range should not be used.
Ordering PCP-capable cups for a program
Our site is built for bulk and recurring orders. Buyers get volume pricing, free shipping on 100+ cups, and same-day dispatch from US stock. We are based in St. Louis, Missouri, and we work with clinics, behavioral health programs, employers, drug courts, corrections and distributors, including multi-site accounts that need a quote.
If PCP is on your panel, start with the 12-panel PCP cup for CLIA-waived point-of-care use, or see the full range on our drug test cups page. For volume terms, visit our wholesale drug test cups page and request a quote.
FAQ
How long do you test positive for PCP?
Most people test positive for about 7 to 14 days after the last use, according to FDA guidance, with first detection around 4 to 6 hours after use (FDA). Some laboratory references describe a shorter window of up to 8 days. Heavy or chronic use can lengthen it.
What can cause a false positive for PCP?
Published reports have linked false-positive PCP immunoassay screens to desvenlafaxine, venlafaxine, dextromethorphan, ibuprofen and tramadol (PMC). GC/MS found no PCP in those cases. That is why a presumptive positive needs confirmation by GC/MS or LC-MS/MS.
Does a negative urine test prove someone never used PCP?
No. FDA explains that a sample can be collected too early or too late, that drugs do not stay detectable forever, and that no drug test is 100% accurate (FDA). A negative means the sample was below the cutoff when tested.
Can a urine test show how much PCP was used or when?
No. Detection in urine indicates recent exposure, but it cannot determine the dose or the route of administration (Ohio State labs). It also does not show current impairment.
Which of your cups is CLIA-waived?
Our 12-panel cup with PCP is CLIA-waived and FDA-cleared. The 12-panel ETG/fentanyl cup, the 14-panel cup and the 16-panel cup are Forensic Use Only and are not CLIA-waived. All results are preliminary, and positives need laboratory confirmation.
Sources
- FDA: Drugs of Abuse Home Use Test
- Mayo Clinic Laboratories: Phencyclidine (PCP)
- Mayo Clinic Laboratories: PCP confirmation, urine
- Drug Detection Windows (drug-free workplace reference)
- SAMHSA: Clinical Drug Testing in Primary Care
- ARUP Laboratories: PCP urine screen with reflex to quantitation
- PMC: False-positive PCP on urine drug screen
- PMC: How often do false-positive PCP urine screens occur
- Ohio State labs: PCP urine confirmation
- I-693 drug disclosure and medication cross-reactivity